Is a Single Light Bulb Really “Ruining Your Health”?
New Scientist August 2026 Cover: A Proposition Worth Taking Seriously—and Testing Against the Evidence
Lawrence Lin | Founder & CEO, Lighting Recipe Studio (LRS) | Founder & Chairman, Good Light Group Asia (GLGA)
Core Judgment: This is not an article to shrug off—and certainly not one to use as a tool for selling lights. The scientific question it raises is worth taking seriously; the causal answer it offers is still far from mature.
Over the past few days, a black-background cover has circulated rapidly across the international lighting and light-health communities on LinkedIn. Beside a hanging light bulb, it asks: “Why this light bulb is wrecking your health.” The article goes further, connecting modern LEDs, insulated glazing, the lack of red and near-infrared light, mitochondrial function, and a chain of purported causal links to diabetes, dementia, cancer, and cardiovascular disease.
This is not a story from a fringe publication. Its author, Graham Lawton, holds a degree in biochemistry from Imperial College London and a master’s degree in science communication. He has worked at New Scientist for many years and received the UK PPA’s Writer of the Year award in 2023. Precisely because of this, the cover has sparked more than simple sharing—it has triggered a serious, highly technical, and at times sharply contested debate over the evidence.
01 | The Real LinkedIn Debate Isn’t About Whether “Red Light Works”
As of the time of writing, a discussion post by German chronobiologist Manuel Spitschan had around 74 comments, while a post by renowned lighting designer Rogier van der Heide had around 70. Participants span chronobiology, vision science, lighting design, architecture and engineering, healthy buildings, and photobiomodulation. For a lighting cover story, this is more than ordinary social-media engagement—it has become a public, cross-disciplinary peer review.
Manuel Spitschan: There Is a Long Evidence Chain Between “Biologically Plausible” and “Harm to Populations”
Spitschan is Professor of Chronobiology and Health at the Technical University of Munich and also leads a research group at the Max Planck Institute. He acknowledges that red and near-infrared light can influence biological processes involving mitochondria, and that photobiomodulation is a legitimate field of research. But he points out that mechanistic experiments, small-scale interventions, associations with daylight exposure, and hypotheses about indoor light spectra represent different levels of evidence. They cannot simply be stitched together to conclude that “LEDs cause metabolic disease.”
His key reminder: Biological plausibility does not equal population-level harm. Correlation does not establish mechanism. And the effectiveness of a particular intervention does not mean that the absence of that intervention constitutes a “nutritional deficiency.”
Rogier van der Heide: Fear Is Not a Lighting Strategy
Rogier has more than 35 years of experience in lighting design. He has led global design teams at companies including Philips and Zumtobel and has received the IALD Radiance Award. His criticism focuses on the way the cover compresses a complex issue: the article discusses LEDs, glazing, daylight, infrared radiation, daily schedules, and architecture as an interconnected system, yet the cover reduces it to a single household light bulb—and, in doing so, creates a health scare.
He supports brighter days, gentler evenings, and better access to daylight. But he rejects slogans such as “ultra-processed light” 或 “95% of the spectrum is lost” when they are not clearly defined and are used in place of actual design strategies.
Kevin Houser: The Industry Has Even Gotten Part of Lighting History Wrong
Houser is a professor of lighting and human factors at Oregon State University and serves as a principal engineer at the Pacific Northwest National Laboratory. He adds an important industry perspective: many buildings transitioned from fluorescent lighting to LEDs, rather than directly from incandescent lighting to LEDs. Fluorescent lamps also do not produce the same rich infrared output associated with incandescent sources.
At the same time, temporal light modulation—often discussed as flicker—introduced by LED drivers may be a more immediate and measurable issue. A sensational “light bulb scare” headline can therefore distract from the health, comfort, and performance questions the industry actually needs to address.
Martin Moore-Ede: Don’t Let Dislike of the Headline Obscure the Potential Risks of Spectral Transition
There is also another side worth hearing. Martin Moore-Ede, head of the Circadian Light Research Center and a former professor at Harvard Medical School, argues that the cover has at least succeeded in drawing public attention to narrow-spectrum blue-pumped LEDs. He emphasizes that the issue is not only the absence of near-infrared light, but also the failure to remove inappropriate short-wavelength light at night.
It is worth noting that his post also promotes his own new book and his “healthy light diet” proposition. That does not automatically invalidate his views, but readers are entitled to understand the broader communication and commercial context surrounding them.
The emerging consensus on LinkedIn, therefore, is not that “LEDs are safe” or that “LEDs are harmful.”
A more accurate consensus is this:
Light is biologically active. Modern indoor light environments deserve renewed scrutiny. But any health claim must specify the spectrum, intensity, timing, duration, direction, site of exposure, and cumulative dose.
Campfires, candles, and incandescent lamps all contain relatively abundant long-wavelength components. But “contains” does not automatically mean “the dose is sufficient” or “the light has a clinically demonstrated effect.”
Image source: provided by the user / original article illustration.
02 | The Article Reveals Three Distinct “Light–Health” Pathways That Are Being Conflated
First: Light Enters Through the Eyes and Acts on the Circadian System
This is currently the relatively mature pathway. Sufficient daytime light exposure to the eyes helps synchronize the circadian system, while light at inappropriate times at night can affect sleep and circadian rhythms.
Relevant metrics include vertical illuminance at the eye, spectral power distribution, melanopic EDI, timing, and duration of exposure. This pathway is fundamentally different from asking how much near-infrared radiation is absorbed by the skin.
Second: Red / Near-Infrared Light Acts Directly on Tissue
This falls under the pathway of photobiomodulation (PBM). Research in this area typically uses specific wavelengths and clearly defined irradiance and energy doses to expose the skin or targeted tissue.
The appropriate measurement language is nm, mW/cm², J/cm², exposure area, and target location—not lux or CCT.
Applying results from therapeutic-dose experiments directly to ordinary indoor lighting is one of the article’s biggest logical leaps.
Third: The Overall Effects of Daylight and Outdoor Environments
Daylight simultaneously changes illuminance, spectrum, temporal dynamics, field of view, physical activity, air quality, temperature, and behavior.
If a daylight group performs better than an artificial-light group, that does not automatically prove that near-infrared light is the sole cause. These studies are highly valuable, but more refined experimental controls are needed to progressively separate the individual factors.
LRS Perspective: A “healthy lighting” question is not yet a verifiable engineering proposition unless we can first answer: Where does the light enter the human body? At what dose? At what time? And what biological target is it acting on?
03 | Put the Key Evidence Back Where It Belongs
The studies cited in the article are not without evidence. But the strength of that evidence is far from sufficient to support the kind of causal conclusions implied by the cover.
670 nm and blood glucose | 30 healthy participants received a 15-minute red-light intervention at approximately 36 J/cm². The incremental area under the postprandial two-hour blood glucose curve decreased by 27.7%, while the peak decreased by 7.5%. This was a clearly dosed, acute photobiomodulation (PBM) experiment—not a study of ordinary indoor lighting.
Daylight and type 2 diabetes | 13 people with type 2 diabetes participated in a randomized crossover study comparing 4.5 days of daylight with 4.5 days of artificial light. One measure within a narrower blood-glucose range improved, but major outcomes such as mean interstitial glucose were not uniformly significant. More importantly, daylight represents an entire exposure environment and cannot be attributed to near-infrared light alone.
Supplementing LEDs with broader-spectrum light and vision | A 2026 Scientific Reports study suggested that supplementing a conventional LED environment with broader-spectrum light may improve color-contrast performance. But the sample was very small, and the findings primarily concern visual performance. They cannot be extrapolated to risks of diabetes, cancer, or dementia.
The overall clinical evidence for PBM | A 2025 umbrella review included 15 meta-analyses, 204 randomized trials, and more than 9,000 participants. Some indications showed positive signals, but the overall evidence was generally low to moderate quality, with substantial heterogeneity in treatment parameters.
What Can We Establish?
Most white-light LEDs produce little to no near-infrared output. That is a measurable spectral fact. Red and near-infrared light can produce biological effects at specific doses, and this is supported by genuine research evidence.
What Can’t We Establish Yet?
“Red-light deficiency” is not yet a recognized medical condition. There is no evidence establishing that the replacement of conventional lighting with LEDs is an important cause of diabetes, dementia, cancer, or cardiovascular disease. Nor is there a generally accepted healthy indoor near-infrared dose threshold.
Plant lighting has already become accustomed to discussing wavelengths beyond the visible spectrum. For human lighting to enter the same level of discussion, the first requirement is more rigorous definitions of exposure and more precise dose measurement.
Image source: provided by the user / original article illustration.
04 | Why China’s Lighting Industry and Academic Community Must Pay Attention
China has the world’s largest LED manufacturing base, supply chain, and application market. If long-wavelength light does prove to have meaningful long-term health value, the implications could be enormous. But if the evidence remains insufficient and is nevertheless packaged as “full-spectrum healthy lighting” 或 “NIR wellness lamps,” the potential for consumer misinformation—and subsequent industry backlash—could be equally significant.
Over the past two decades, we have optimized LEDs to be more efficient, more affordable, longer-lasting, and easier to control. None of these achievements is a mistake. But the industry’s evaluation framework still revolves primarily around luminous efficacy, illuminance, CCT, color rendering, glare, and cost.
Even as we move into “healthy lighting,” many projects still stop at melanopic EDI or a single “circadian mode” button.
The debate over near-infrared light now reminds us of something important:
We may not yet be measuring “light” completely.
Traditional visual and circadian metrics primarily address the visible spectrum and ocular exposure.
Tissue effects from red and near-infrared light require consideration of irradiance, energy dose, geometry, body location, and time-integrated exposure.
“Full spectrum” cannot be defined simply by visual continuity, high CRI, or a color temperature close to daylight.
Glazing, shading, interior materials, distance, and direction can all change the actual broad-spectrum exposure reaching the human body.
05 | What LRS and GLGA Are Building Is Not Another Slogan, but a New Evidence Infrastructure for Light
From traditional lighting and the transformation of the LED industry to the founding of LRS, I have watched the industry repeatedly compress complex questions into a single selling point.
But lasting intellectual credibility is rarely built by being the first to announce a conclusion. It is built by being the first to establish a common language, reliable measurement methods, and robust validation processes.
01 | Establish a “Two-Layer Light Exposure” Framework
Record ocular/circadian exposure separately from skin/tissue broad-spectrum exposure.
The former can use metrics such as melanopic EDI; the latter should extend to spectral irradiance and cumulative energy dose in the red and near-infrared ranges.
02 | Advance Broad-Spectrum Measurement Research Across 380–1700 nm
The next step for LRS should be to extend its existing capabilities in visible-light measurement, color quality, temporal light modulation, and HCL into a research-grade workflow covering the visible spectrum, IR-A, and portions of IR-B.
The goal is not to “prove” a product’s efficacy.
The first goal is to establish what light is actually present in the environment—and how much the human body may actually receive.
03 | Design Controlled Experiments Where Visible Light Is Equivalent but Near-Infrared Exposure Differs
Keep illuminance, CCT, color rendering, melanopic EDI, and temporal light modulation as consistent as possible while varying only the near-infrared dose.
Then separately examine visual, metabolic, sleep, and subjective comfort outcomes.
This is the kind of experimental design that could begin to identify the independent contribution of NIR.
04 | Build a Database Based on Real-World Chinese Environments
Offices, schools, hospitals, senior-care facilities, homes, industrial spaces, and transportation hubs should all be measured across the full day, with broad-spectrum measurements taken at multiple occupant positions—rather than measuring a single workplane illuminance value only at project acceptance.
05 | GLGA to Build a Cross-Disciplinary Community
Bring together researchers and practitioners from photobiology, chronobiology, endocrinology and metabolic medicine, ophthalmology, optical metrology, building science, lighting design, controls, and standards organizations to jointly establish research agendas, terminology, reporting templates, and conflict-of-interest disclosure rules.
The next step for healthy buildings is not to add another “healthy lighting” label to a luminaire.
It is to connect daylight, spectrum, time, space, and operational verification into one integrated system.
Image source: King’s College Hospital NHS Foundation Trust / provided by the user.
06 | Conclusion: The More Invisible the Light, the More Visible the Evidence Needs to Be
I do not believe we have enough evidence today to declare that “LEDs are destroying our health.” Nor do I believe the industry should retreat to the old defensive position that says, “As long as a product meets lighting standards, it has nothing to do with health” simply because a headline is exaggerated.
What this cover truly exposes is the knowledge boundary of the lighting industry.
We have become highly proficient at measuring the light that the human eye sees. Yet we are still not very good at describing the totality of light that the human body actually receives over the course of a day.
We are beginning to talk about health outcomes, but we still lack a shared language for dose, timing, pathways, and validation.
The worst thing the Chinese lighting industry could do is quickly manufacture another wave of “red-light mythology.”
The most valuable thing we could do is leverage our extensive supply chain, diverse application environments, and strong research capabilities to turn this question into a reproducible, comparable, and verifiable research program.
Call to Action
GLGA is open to working with Chinese and international organizations across photobiology, chronobiology, medicine, metrology, design, manufacturing, and standards to develop a research agenda for “indoor broad-spectrum light exposure and health.”
LRS is prepared to contribute the foundational work in measurement, data collection, and real-world validation.
We are not in a hurry to prove how miraculous red light might be.
First, let’s measure the light we cannot see.
What we should perhaps be most concerned about is not any particular light bulb.
It is that while the scientific boundaries remain unclear, we continue to use familiar metrics and pretend that we have already measured the whole of light.
Author Bio
林纪良 is the Founder & CEO of 光配方研究院(Lighting Recipe Studio, LRS), Founder & Chairman of Good Light Group Asia (GLGA), Board Member of Good Light Group, and a WELL Light Concept Advisor for IWBI. He previously served as Global CEO of LEDVANCE.
His work focuses on translating research on light and health into lighting practices that are measurable, designable, deliverable, and verifiable.
Disclosure
LRS develops measurement tools for spectrum, color quality, temporal light modulation, and healthy lighting. As a result, LRS has a clear professional and commercial interest in the question of expanding the boundaries of light-environment measurement.
This article does not constitute medical advice, nor does it endorse the health benefits of any specific light source or near-infrared product.
The LinkedIn comments referenced in this article are translated excerpts or summaries of publicly available posts. Engagement figures are dynamic and may change over time.
Key References & Public Discussions
New Scientist original article (Graham Lawton, August 10, 2026): https://www.newscientist.com/article/2582914-the-shock-revelation-that-light-bulbs-are-wrecking-your-metabolism/
Public archive of the original article: https://archive.ph/lvNDq
Manuel Spitschan’s LinkedIn discussion: https://www.linkedin.com/posts/spitschan_there-is-an-interesting-scientific-question-activity-7495302203025379328-oqzn
Rogier van der Heide’s LinkedIn discussion: https://www.linkedin.com/posts/rogiervanderheide_new-scientist-i-think-we-need-to-talk-activity-7495395143349633024-2pel
Martin Moore-Ede’s LinkedIn discussion: https://www.linkedin.com/posts/martin-moore-ede-80630a12_the-recent-new-scientist-magazine-cover-story-activity-7496213907687030787-EEmH
Powner & Jeffery: 670 nm and blood glucose (Journal of Biophotonics, 2024): https://doi.org/10.1002/jbio.202300521
Harmsen et al.: Natural daylight and type 2 diabetes (Cell Metabolism, 2026): https://doi.org/10.1016/j.cmet.2025.11.006
From the simple slogan of “healthy lighting” to a comprehensive, practical methodology for designing, measuring, and verifying light.
By 林纪良 Chairman, GLGA · Board Member, GLG · IWBI WELL Light Concept Advisor · Founder & CEO, LRS
Over the years, whenever the conversation turns to 健康照明, it quickly comes back to a familiar set of terms: full-spectrum light, eye protection, blue-light reduction, daylight simulation, and automatic color-temperature adjustment. None of these ideas are necessarily wrong, but they often make a complex subject seem far simpler than it really is.
Light does affect us. But getting from “light has an effect” 至 “how should light actually be designed?” is a much longer journey. It requires understanding how light enters the eye, when and where a person is exposed to it, what they are doing at the time, and how long that exposure lasts. It also requires a way to translate design goals into something that can be calculated, specified, procured, commissioned, and ultimately verified on site.
《Understanding Light》 is written precisely for this often-overlooked journey.
Across these 18 articles, we move beyond slogans and familiar claims to build a more complete framework for understanding, designing, measuring, and verifying healthy lighting.
Why Start with the Fundamentals?
The lighting industry does not lack new concepts. What it lacks is the ability to put those concepts in the right context.
Some treat color temperature as a prescription for circadian rhythms. Others use 500 lux at the desk to conclude that the eyes have received enough light. Still others see a mel-EDI value and rush to translate it into claims about sleep, mood, or productivity. The result is an ever-growing vocabulary of technical terms, but not necessarily more reliable judgment.
The value of foundational knowledge is not to turn everyone into a photobiology researcher. It is to develop several essential forms of discernment: understanding what lux can—and cannot—tell us; recognizing that CCT and spectrum are not the same thing; knowing that scientific consensus, technical standards, building certifications, and product marketing each have their own boundaries; and, above all, understanding that health-related claims must never go beyond the evidence.
That is why this series returns to one principle again and again:
Method before instrument. Evidence before claims.
The 18 Articles Answer Four Fundamental Questions
1. How Does Light Actually Affect People?
Articles 1–4 begin with the point that is most often overlooked: Can a light really be called “healthy”? Why are the eyes responsible for more than simply seeing? How does light influence alertness, sleep, and the circadian rhythm? And why can the same light produce different outcomes depending on age, light history, and individual conditions?
This section is not intended to make light seem mysterious or complicated. Rather, it reminds us of something fundamental: people are not standardized light receptors. Before discussing healthy lighting, we must first distinguish between visual effects, non-visual effects, and actual health outcomes.
2. How Do We Understand Metrics, Research, and Standards?
Articles 5–9 address the language of measurement that the industry most needs to strengthen.
How much optical information should a lighting study report? Why aren’t lux and CCT enough? What do mel-EDI 和 mel-DER actually represent? How should recommended values such as 250, 10, or 1 be interpreted? And why should standards, guidelines, certifications, and regulations never be treated as interchangeable?
The goal of these articles is not to require everyone to memorize formulas. It is to give designers, product managers, testing professionals, and procurement teams a common language.
Only when definitions are consistent can data be meaningfully compared. And only when measurement conditions are clearly defined can results be independently verified.
3. What Do the Industry’s Most Popular Claims Really Mean?
Articles 10–15 return to real-world projects and consumer communication, examining some of the industry’s most widely used terms and claims.
Why does 500 lux at the desk not necessarily mean the eyes are receiving 500 lux? Why must integrated lighting first satisfy the fundamentals of good lighting? How should full-spectrum, color temperature, and blue light be discussed accurately? Why can invisible flicker still be a quality issue? And how should daylight, electric light, and lighting controls work together?
This section may make some familiar claims less convenient to use. That is precisely the point of professionalism.
Professionalism is not about making complex issues sound mysterious. It is about simplifying where simplification is appropriate—and refusing to skip steps where they matter.
4. How Do We Turn Knowledge into a Complete Project Methodology?
Articles 16–18 bring everything back to the real world of project delivery.
First, requirements are defined through a five-dimensional framework of light, people, space, time, and activity. Those requirements are then translated into system specifications that can be calculated, specified, and procured. Finally, the process is closed through design, commissioning, measurement, and post-occupancy verification.
At this point, healthy lighting is no longer about a single LED, a particular spectrum, or a measurement instrument.
It is a system that must continuously work.
And that system must stand up to scrutiny at every stage—from drawings and mock-ups to the actual site and real human behavior.
Who Is This Series For?
如果您是 lighting industry leader, this series can help you think about where your organization’s capabilities need to be built for the future—not simply chase the next market buzzword.
If you work in R&D or product development, it can help you translate the concept of “healthy lighting” into measurable product data, operating conditions, and clearly defined boundaries of application.
如果您是 designer, consultant, or engineer, it provides a path from human needs to eye-level measurements, lighting scenarios and controls, and on-site verification.
If you work in architecture, interior design, healthcare, education, senior living, or public-sector management, you don’t need to start with formulas. Begin with five questions:
Who is the lighting for? Where are they? What time is it? What are they doing? And how will we prove the result?
And for everyday readers, the series offers a simpler way to think about lighting claims. When you encounter terms such as “eye protection,” “sleep support,” “blue-light reduction,” or “full spectrum,” you don’t need to immediately believe them—or dismiss them.
Instead, ask:
For whom? At what dose? For how long? In what context? And based on what evidence?
That is where better lighting decisions begin.
Read It from Start to Finish—or Start with the Question You Have
Reading all 18 articles in sequence creates a complete journey—from the mechanisms of light, through measurement, to design and verification. But this is not a textbook that must be read from the first page to the last.
If you are evaluating products, start with the articles on full-spectrum light, blue light, and flicker.
If you are working on a project, begin with eye-level measurement, the five-dimensional framework, and the verification process.
If you need to understand standards and recommendations, start with mel-EDI, recommended values, and the hierarchy of standards and guidance, then return to the fundamentals of human responses to light.
What matters is not memorizing every technical term. It is gradually developing a better way to ask questions:
What are we measuring? Where are we measuring it? When are we measuring it? For whom does it apply? And how far does the evidence actually support the claim?
After the 18 Articles, We Are Still Only at the Beginning
The end of foundational knowledge is not a certificate declaring that something is “healthy lighting.” It is the ability to begin confronting the complexity of the real world.
Offices, schools, hospital wards, senior living facilities, hotels, and homes will never share a single universal lighting formula. Children, adults, older people, night-shift workers, and patients should not be reduced to the same number, either.
What is more important for the future is to develop application models tailored to different people and contexts—models that can be continuously measured, evaluated, and refined through feedback.
That is why these 18 articles are both a foundation and an invitation to the industry:
Less competition between slogans and terminology. More definitions, data, and evidence from the field.
Less asking:
“Which light is the healthiest?”
More asking:
“For this person, in this place, at this time, and for this activity, what light is appropriate?”
Making Light Clear is not about making things sound more complicated.
Quite the opposite.
It is about making every design decision, procurement choice, and product claim closer to reality—and more capable of standing up to scrutiny over time.
Three Things to Do Before Reading This Series
Start with the articles most relevant to your current work. There is no need to read them strictly in sequence simply for the sake of following the order.
Whenever you encounter a healthy-lighting metric, record the context. Note the subject, measurement location, direction, time, activity or scenario, and measurement conditions alongside the number.
Bring the distinction between “what we can say today” and “what we cannot yet say” into your work. Apply it to product meetings, design reviews, and external communications.
Evidence Label: Series Guide
This article explains the structure, reading approach, and boundaries of 《Understanding Light》, an 18-part series. It is intended as a guide to the series and does not constitute a lighting prescription for any specific population or project.
Key References
CIE S 026:2018 — CIE System for Metrology of Optical Radiation for ipRGC-Influenced Responses to Light CIE S 026:2018
CIE PS 001:2024 — CIE Position Statement on Integrative Lighting: Recommending Proper Light at the Proper Time CIE PS 001:2024
Brown et al. (2022) — Recommendations for daytime, evening, and nighttime indoor light exposure Brown et al. (2022) — PLOS Biology
Establishing a complete evidence chain connecting light source characteristics, spatial conditions, eye-level exposure, and human-factor responses
Healthy Lighting Leaves Behind “Everyone Speaking a Different Language.”
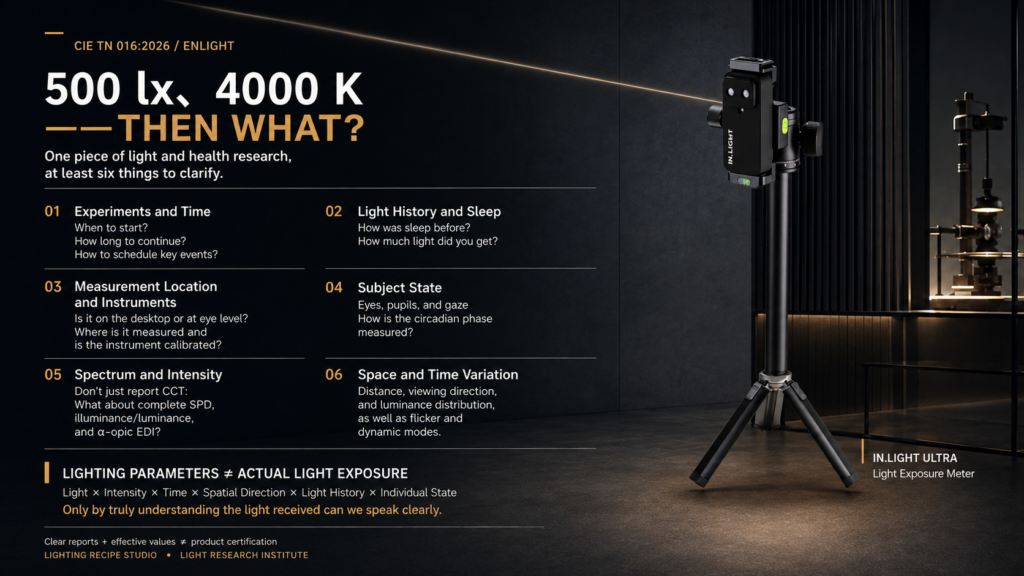
CIE TN 016:2026 introduces the first comprehensive framework for reporting and validating light interventions—moving beyond “500 lx, 4000 K” to a complete evidence chain encompassing light source, spatial environment, eye-level light exposure, and human responses, and establishing a common language for comparable and reproducible light and health research.
By Lawrence Lin | Chairman, Good Light Group Asia (GLGA), Board Member, Good Light Group (GLG), IWBI WELL Light Concept Advisor, Founder & CEO, Lighting Recipe Studio (LRS)
In many studies on light and health, the experimental conditions are often described as follows: 4000 K, 500 lx, with a two-hour exposure. At first glance, this appears to be sufficiently specific.
But where was the 500 lx measured? Was it on the horizontal workplane or on the vertical plane at the observer’s eye? Where was the participant looking? What spectral power distribution actually reached the eyes? What was the melanopic Equivalent Daylight Illuminance (mel-EDI)? At what point in the participant’s circadian cycle was the experiment conducted? What kind of light exposure had the participant experienced beforehand?
If these questions remain unanswered, another research team may be unable to reproduce the study—even if it uses the same correlated color temperature, illuminance, and exposure duration.
This is precisely the challenge that the International Commission on Illumination (CIE) seeks to address with its newly released CIE TN 016:2026.
It does not propose a new “healthy lighting metric,” nor does it claim that any particular type of light is definitively effective. Instead, it accomplishes something more fundamental—and more important: before discussing how light affects people, it first makes clear exactly what light people are actually exposed to.
1. CIE S 026 Gives Us a Measuring Stick; TN 016 Begins Standardizing How We Record the Measurements
The full title of CIE TN 016:2026 is AComprehensive Checklist for Reporting Light Characteristics in Laboratory-Based Human Studies Using Light As An Intervention. The document incorporates the ENLIGHT (Expert Network on LIGHT Interventions) consensus checklist into the CIE technical document framework for laboratory-based human studies that use light as an intervention.
CIE positions it as the first internationally endorsed consensus checklist for reporting light interventions.
The relationship between these two documents can be summarized in one sentence:
CIE S 026:2018 established the α-opic system for quantifying how visible light stimulates the five classes of photoreceptors in the human eye, whereas CIE TN 016:2026/ENLIGHT establishes a common language for how researchers should comprehensively document and report experimental conditions when using these quantities.
The former is essentially a measuring stick; the latter requires researchers to explain where the measurement was taken, in which direction, at what time, with what instrument, and under what conditions the participant received the light exposure.
TN 016 is not intended to replace existing documents. CIE TN 011:2020 discusses which factors should be recorded and reported in studies involving intrinsically photosensitive retinal ganglion cells (ipRGCs), while CIE TN 012:2021 provides guidance on measuring temporal light modulation. TN 016 consolidates these recommendations into a practical checklist that can be systematically followed.
The ENLIGHT checklist was developed through a four-round modified Delphi consensus process involving international experts. The first round included 65 participants with experience in human light intervention research. The process ultimately produced a checklist of 25 reporting items, which was subsequently tested and refined by independent experts.
The original consensus paper was published in 2023, and in 2026 it was formally issued by CIE as a Technical Note, aligning it with CIE’s existing framework for light measurement and reporting.
Its significance does not lie in introducing new terminology. Rather, it provides a common reporting framework that makes data generated by different laboratories easier to interpret, compare, and reproduce, thereby increasing their suitability for inclusion in systematic reviews and meta-analyses.
2. What Has Been Missing Is Far More Than a Spectral Distribution Curve
"(《世界人权宣言》) 25 reporting items in the ENLIGHT checklist can be broadly divided into two domains: study conditions 和 light characteristics. For readers in the lighting industry, they can be understood as six categories of information.
1. Experimental and Timing Conditions
This category includes the experimental setting, the timeline of key events, and the timing and duration of the light intervention.
The physiological effects of light are highly time dependent. Light delivered in the morning, during the daytime, or immediately before bedtime cannot be regarded as the same biological stimulus, even when its physical parameters are identical.
2. Prior Light Exposure and Sleep Status
This includes participants’ sleep–wake or activity patterns before entering the laboratory, their previous light exposure history, and the light environment immediately preceding the intervention.
Human responses to a given light exposure depend not only on the light being presented at that moment but also on prior light exposure and sleep history.
3. Measurement Location, Direction, and Instrumentation
This category specifies whether measurements were made on a horizontal or vertical plane, the position and orientation of the sensor, and the model and calibration status of the measurement instrument.
Although these may appear to be routine experimental details, they determine whether the recorded values accurately represent the light actually received by the participant.
A measurement of 500 lx on a workplane does not automatically correspond to 500 lx entering the eye.
4. Participant Characteristics
This includes ocular health and visual function, pupil status, and the timing of the light intervention relative to the participant’s sleep schedule or circadian phase.
Measurements taken at eye level provide an important proxy for ocular light exposure, but they are not equivalent to the retinal light dose actually received by each individual. Pupil size, age, ocular media transmittance, and individual differences in photosensitivity all influence the ultimate biological response.
5. Spectral, Photometric, and Color Characteristics
This category includes illuminance/luminance, spectral irradiance/radiance distributions, α-opic irradiance/radiance, α-opic Equivalent Daylight Illuminance (EDI) and Equivalent Daylight Luminance (EDL), as well as chromaticity, correlated color temperature (CCT), peak wavelength, bandwidth, and color rendering properties.
This further illustrates that CCT describes the appearance of light but cannot, by itself, characterize its biological effects on humans. Likewise, the term “full spectrum” cannot substitute for a complete spectral power distribution (SPD) together with α-opic quantification.
6. Spatial and Temporal Characteristics
This includes the position of the light stimulus relative to the participant, viewing distance, whether the light is viewed directly or indirectly, the stimulus size within the visual field, and its temporal properties such as flicker frequency, waveform, and modulation pattern.
For tunable-white, multi-channel, and dynamic lighting systems, reporting only a nominal CCT or a single static operating condition is clearly insufficient to reconstruct the actual light intervention.
Taken together, these categories define the true light-dose conditions in a human intervention study:
Light dose = Spectrum × Intensity × Time × Spatial geometry and direction × Prior light exposure history × Individual physiological state.
3. A Luminaire’s Specifications Are Not the Same as a Person’s Light Dose
This is perhaps one of the most important messages that CIE TN 016 offers to the lighting industry.
The spectral power distribution (SPD) emitted at a luminaire’s aperture is not the same as the SPD reaching the eye. Likewise, horizontal workplane illuminance is not equivalent to the amount of light that actually enters the eye.
Once light leaves the luminaire, it is modified by viewing distance, angle, obstructions, surface reflectance, spatial distribution, and the observer’s viewing direction before ultimately determining the eye’s actual light exposure.
As a result, the same luminaire installed in different spaces—or even the same person looking in different directions within the same space—may experience substantially different melanopic Equivalent Daylight Illuminance (mel-EDI) at the eye.
Similarly, two lighting scenarios may have identical illuminance and correlated color temperature (CCT), yet differ in their spectral power distributions (SPDs) and, consequently, their α-opic stimulation.
TN 016 does not require every study to measure eye-level exposure at a fixed height. However, it explicitly includes the measurement plane, measurement location, and viewing direction in its reporting checklist, requiring these details to be documented whenever applicable.
This elevates actual ocular light exposure from a frequently overlooked experimental detail to a core requirement for research reproducibility.
For the lighting industry, this also carries an important implication: healthy lighting cannot stop at the relationship between luminaire specifications and control commands.
What must ultimately be established is a complete chain linking:
Light source and control state → Spatial distribution of light → Actual ocular light exposure → Human physiological and psychological responses
If any link in this chain is not accurately characterized or documented, the health-related conclusions drawn from the subsequent stages inevitably become less reliable and less interpretable.
4. Its Impact Extends Well Beyond Scientific Publications
Although CIE TN 016 is primarily intended for scientific research, its influence is unlikely to be confined to the formatting of research papers. Its implications extend across the entire lighting ecosystem.
For Research Institutions
The conditions of a light intervention should be comprehensively planned from the earliest stages of study design and grant proposal development—not reconstructed later when preparing a manuscript for publication.
More transparent reporting improves the reproducibility of experiments, facilitates the identification of potential confounding factors, and increases the likelihood that datasets can be incorporated into systematic reviews and meta-analyses.
For Measurement Instrument Manufacturers
In the future, valuable research data will consist of far more than a single number displayed on an instrument.
Raw spectral power distributions (SPDs), α-opic metrics, measurement location and orientation, timestamps, instrument serial numbers, calibration status, and algorithm versions will all become essential components of data traceability.
For Luminaire, Light Source, and Lighting Control Manufacturers
For tunable-white, multi-channel, and dynamic lighting systems, it will no longer be sufficient to provide only a nominal correlated color temperature (CCT), an initial lumen output specification, or a static photometric file.
Instead, a verifiable relationship must be established between the control commands, channel operating states, the resulting SPD, and the actual ocular light exposure experienced within the space.
For Lighting Designers and Healthy Building Professionals
Calculated design values are not equivalent to the light exposure that occupants actually receive.
Meeting workplane illuminance requirements does not necessarily mean that eye-level melanopic Equivalent Daylight Illuminance (mel-EDI) achieves the intended target.
Design, commissioning, operational control, and on-site verification should therefore be integrated into a single closed-loop workflow.
For Product Claims and Marketing
Any claims related to sleep, circadian regulation, alertness, mood, or cognitive performance will increasingly need to satisfy more rigorous evidentiary standards.
A single set of luminaire specifications, one short-term measurement, or an isolated correlation study is unlikely to provide sufficient evidence for robust causal claims.
TN 016 will not become a product regulation overnight. However, it is likely to steadily raise the evidentiary threshold for research collaborations, peer review, product validation, and health-related marketing claims.
5. Equally Important: What TN 016 Does Not Specify
The more influential a document is, the more important it becomes to avoid overinterpreting its scope.
First, TN 016 is a guidance document, not a mandatory international standard. As a CIE Technical Note, it explicitly states that its recommendations are advisory rather than normative and are not intended as mandatory requirements.
Second, it is a reporting checklist—not a scoring system for research quality. Thoroughly documenting that a particular experimental condition was not controlled does not automatically make a study well designed. It does, however, enable readers to correctly assess the study’s scope, limitations, and potential sources of confounding.
Third, it does not prescribe target values. TN 016 does not specify how much melanopic Equivalent Daylight Illuminance (mel-EDI) should be achieved during the daytime, evening, or before sleep, nor does it establish pass/fail criteria for luminaires, lighting systems, or measurement instruments.
Fourth, there is currently no such thing as “CIE TN 016 certification” or an “ENLIGHT-certified product.” A more accurate description would be that a particular study or measurement system supports the recording and reporting of light exposure in accordance with the ENLIGHT/CIE TN 016 recommendations.
Fifth, the document is intended primarily for laboratory-based human light intervention studies and should not be interpreted as a building lighting design guideline. Real-world environments involve daylight, mixed lighting, occupant behavior, and long-term exposure patterns that require additional field studies and continuous monitoring methods to characterize adequately.
Finally, although eye-level mel-EDI provides a more accurate description of the external light stimulus reaching the eye, a single measurement cannot by itself demonstrate a health outcome. Human responses to light still require rigorous experimental design and should be validated using complementary evidence, including physiological measurements, biomarkers, behavioral outcomes, and assessments of brain function.
6. From “Measuring the Luminaire” to an Evidence Chain Linking Light Source, Space, Ocular Exposure, and Human Response
For 光配方研究院(Lighting Recipe Studio, LRS), the release of CIE TN 016 further reinforces a direction we have long advocated: healthy lighting should not stop at characterizing the light source itself. Instead, it should establish a complete evidence chain that connects the light source and its control state, the spatial distribution of light, the actual light exposure at the eye, and ultimately human physiological and behavioral responses.
To support this evidence chain, the In. Licht product family is being developed with complementary measurement and validation capabilities at different levels:
In. Licht Ultra provides reference characterization of spectral power distributions (SPDs), α-opic quantities, and lighting conditions under different optical fields and control states.
In. Licht Pro enables on-site and time-series monitoring of eye-level illuminance, correlated color temperature (CCT), and melanopic Equivalent Daylight Illuminance (mel-EDI).
In. Licht Well is designed for long-term monitoring of ambient lighting conditions and proxy measurements of ocular light exposure at fixed locations, while simultaneously recording environmental covariates such as indoor air quality.
Looking ahead, the industry’s priority should not be to introduce ever more sophisticated-looking metrics. Rather, it should be to integrate measurement location, measurement direction, timestamps, instrument calibration records, algorithm versions, scene commands, and lighting control states into a unified reporting workflow.
Every dataset should be able to answer a series of fundamental questions:
Where was the measurement taken?
In which direction was it measured?
When was it measured?
What were the lighting source and control settings at that moment?
What light actually reached the participant’s eyes?
Only when these details can be preserved, exported, compared, and verified in real-world environments does measurement become more than the production of a single number—it becomes the foundation of cumulative scientific evidence.
Conclusion: The Lighting Industry Does Not Lack Concepts—It Lacks Accumulating Evidence
The field of healthy lighting has no shortage of concepts, nor does it lack metrics.
What remains genuinely scarce is evidence that can be reproduced, compared, independently verified, and accumulated over time.
CIE TN 016:2026 does not offer the industry a simple answer. Instead, it poses a more fundamental challenge:
Being able to measure something does not mean its effectiveness has been demonstrated. But if we have not even measured the light that people actually receive, meaningful validation is impossible.
When light sources, control systems, spatial light distribution, ocular light exposure, and human-factor research are connected through a single traceable evidence chain, healthy lighting can begin to move beyond marketing narratives and become firmly grounded in scientific research, lighting design, architecture, clinical practice, and public health.
At 光配方研究院(Lighting Recipe Studio, LRS), we look forward to working with research institutions, lighting manufacturers, lighting control companies, measurement instrument partners, and healthy building organizations to advance this vision. Our goal is to ensure that data generated in light-and-health research become genuinely usable, comparable, and verifiable—so that good light is no longer merely a claim, but something that can be measured, validated, and consistently delivered.
We've detected you might be speaking a different language.
Do you want to change to:









 English
 Chinese (Taiwan)
 Chinese (China)
 German